Machines
A Setting Is Not a Promise: Inspecting the Hinge
A pancreatic-cancer patent arrives after years of bold blood-test bets, where the gap between a promising signal and safe screening remains vast.

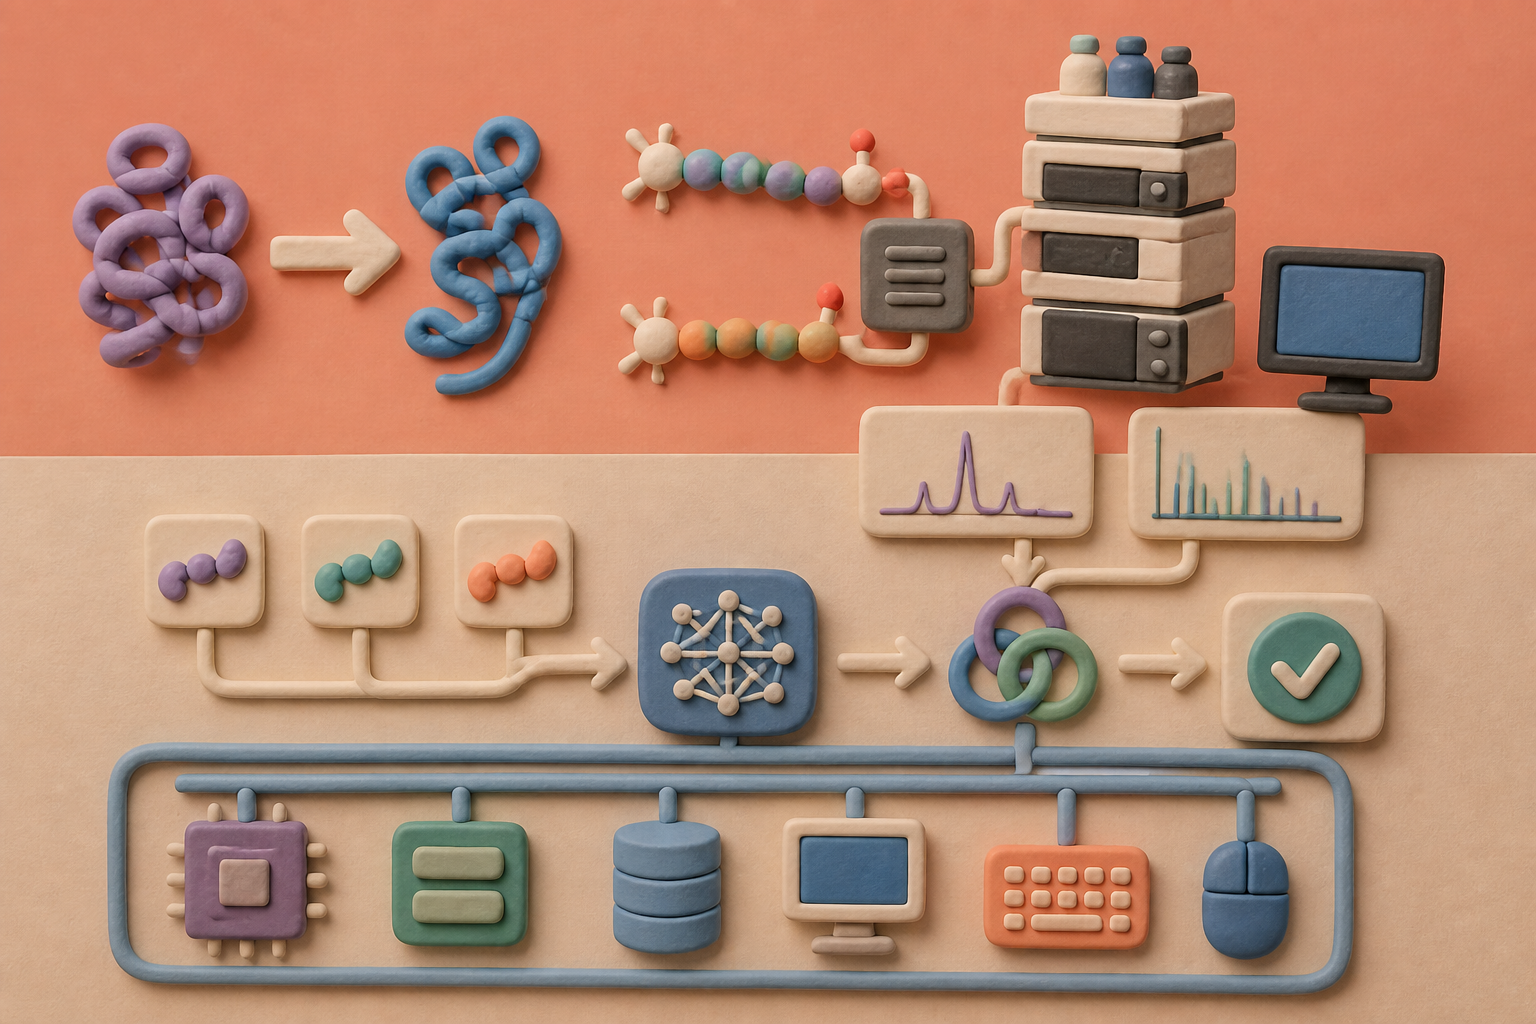
What changes in this design
A reader might expect a pancreatic cancer diagnosis to come directly from one test result or one kind of information.
Here, information about at least three chosen small protein-related pieces is used to create a disease indicator, an intermediate result used to generate the diagnosis output.
That is worth knowing because the diagnosis output comes after information from at least three chosen protein-related pieces is used to create an intermediate indicator. What the indicator measures is not stated.
The first doctor visit
The number I started with makes every pancreatic-cancer test feel urgent: roughly half of patients have advanced disease by the time they first see a doctor. Five-year survival is reported at 13% overall, but about 83% for stage IA disease. A diagnosis from a simple biological sample has such pull that I can understand why. That pull is mine too. But early detection is not automatically good screening. In 2019, a national preventive-services panel concluded that screening asymptomatic adults was likely to bring no more than small benefit and at least moderate harm. Even high-risk programs found only 15.6 cases per 1,000 people screened. Those numbers, to me, are the threshold every new test has to clear.
A $201 million turn
By August 2021, the business behind this application had raised $201 million for a glycoproteomics platform pairing mass spectrometry with machine learning and being discussed across 16 oncology uses, including pancreatic cancer detection. The application is assigned to Venn Biosciences, the patent-holding entity for InterVenn. At the start of 2023, it had already launched laboratory-developed tests for melanoma and ovarian cancer, and planned a colon-cancer test later that year. In January, InterVenn replaced its founder-CEO with its chief operating officer to push commercialization. A second chief executive arrived that September, hired to move work from research settings into clinical pathways. Leadership changes don't tell us whether a test works; I won't pretend otherwise. Those changes do, I think, place this filing in a moment when laboratory promise was under pressure to become patient care.
November 30, 2022
That is why I see US20260253677A1, filed on November 30, 2022 and claiming priority to a November 30, 2021 provisional application, as a record of a particular bet rather than a finished diagnostic. It takes peptide structure data from a person's biological sample and uses at least three selected peptide structures, targeted measures of site-specific protein glycosylation, and a supervised machine-learning system to produce a pancreatic-cancer indicator and then a diagnosis output. The filing reflects, to me, a serious effort to move beyond one familiar marker. This filing doesn't let me infer how its results would hold up in a real-world screening population. Evidence that it can safely screen people without symptoms, sort every confusing look-alike, or improve outcomes on its own is not what I see here.
The test that stopped selling
That caution is not theoretical. In July 2023, Immunovia stopped US commercialization of IMMray PanCan-d, a pancreatic-cancer laboratory-developed blood test launched nearly two years earlier. It cited reliance on CA19-9 and inaccurate results for people who do not produce that marker. A 2025 review says 5% to 10% of patients are Lewis antigen-negative and cannot synthesize CA19-9. The race has not ended: Avantect reported an independent 1,445-person validation cohort with 82.6% overall sensitivity, 76.8% sensitivity for stage I-II disease, and 97.5% specificity. Those figures draw attention, and I can see why. Specificity matters because a false positive does not remain a number once it reaches a clinic. But the review's warning that retrospective, single-center panels can overstate accuracy through spectrum bias and often weaken in realistic populations carries more weight with me. It says screening demands specificity near 99%.
The part worth watching
The useful question, I think, is not whether the filing found an interesting signal. It may have found one worth studying. The question is whether a locked test, tried in the people who would actually receive it, can show that it finds disease earlier without setting off more harm than benefit. Prospective, multi-site evidence in a representative intended-use population, with false positives accounted for alongside sensitivity, is what I would want. Knowing who was missed and what followed a positive result is also something I would want. The route to patients is something I will also watch. A federal final rule issued in 2024 treated in vitro diagnostics as devices even when a laboratory manufactures them; its announced schedule put moderate- and low-risk laboratory-developed tests on a path to premarket review by May 6, 2028. That does not validate this test. It sharpens the line for me: a patent can define a bet, while clinical evidence must earn the right to act on it.
Sources
Reporting for this piece drew on the published filing and the references below.
- Diagnosis Of Pancreatic Cancer Using Targeted Quantification Of Site-Specific Protein Glycosylation
- US20260253677A1 patent record
- InterVenn raises $201m to develop liquid biopsy assay
- InterVenn Biosciences Enters Next Stage with Senior Management Team Updates Focused on Commercialization
- InterVenn Biosciences Welcomes Joshua Stahl as CEO
- Immunovia to Significantly Restructure to Focus Resources on its Next-Generation Blood Test for Pancreatic Cancer Detection
- ClearNote Health to Present Pancreatic Cancer Blood Test Data at ASCO 2026
- Screening for Pancreatic Cancer: USPSTF Reaffirmation Recommendation Statement
- Liquid biopsy and biomarkers in pancreatic ductal adenocarcinoma: from concept to clinical translation
- Prioritizing Early Detection to Improve Survival Outcomes in Pancreatic Cancer
- Medical Devices; Laboratory Developed Tests
The record, briefly. US20260253677A1, “Diagnosis Of Pancreatic Cancer Using Targeted Quantification Of Site-Specific Protein Glycosylation” Receives peptide structure data from a subject's biological sample and uses a supervised machine learning model to generate a pancreatic cancer disease indicator from at least three selected peptide structures, then generates a diagnosis output from that indicator.
Identity details. The saved title-page transcription needs review, so names are not repeated here. Check the official published title page.
More angles on this
- A Handoff Worth Watching: Fragment-Based Drug Design With an Assistant at the BenchAnother reading from the same G16B classification family, bioinformatics.
- Measurement And Analysis Method For Detecting And Quantifying Makes a Small Case for Better TimingAnother reading from the same G16B classification family, bioinformatics.
- CPC G16B: BioinformaticsThe official classification family this record was filed into, published in the USPTO Cooperative Patent Classification scheme.
- CPC G01N: Investigating or analysing materials by determining their chemical or physical propertiesThe official classification family this record was filed into, published in the USPTO Cooperative Patent Classification scheme.
- Methods For Treatment Of Thyroid Cancer Treats the Relationship as the PointAnother reading from the neighbouring G16Z classification family, information and communication technology [ict] specially adapted for specific application fields.
Read around this one:Public patent recordUSPTO published figure